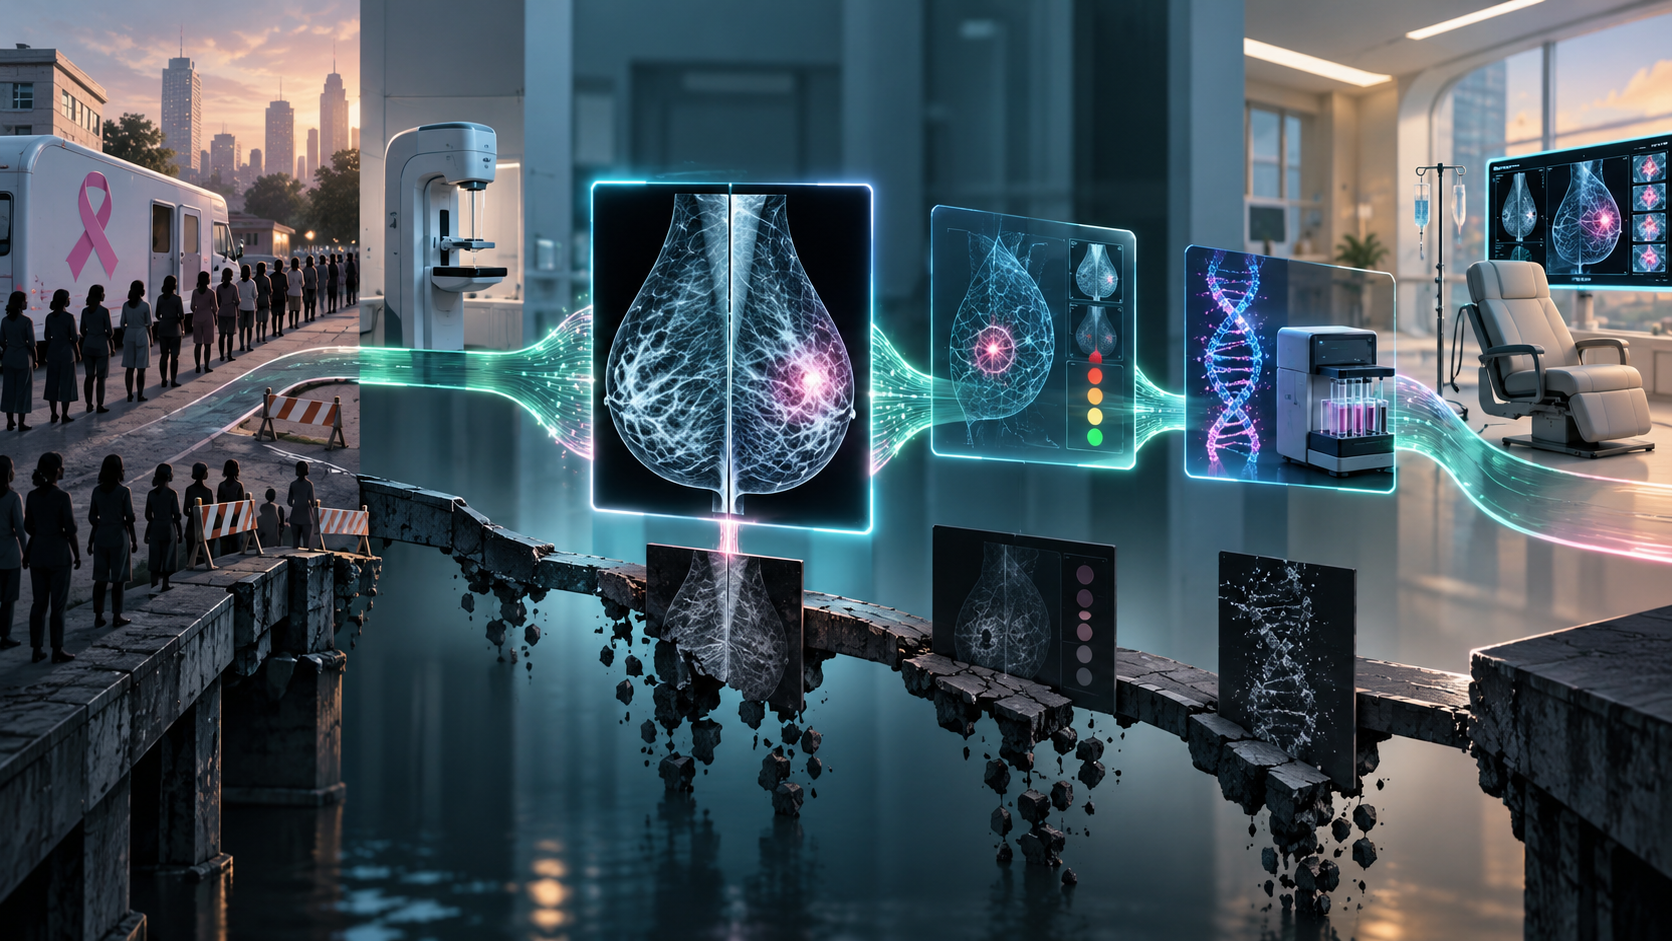
AI applications are being positioned across several stages of breast cancer care, from screening and risk assessment to treatment decisions. The operating question is whether these tools can address specific workflow barriers without turning a broad care journey into an unsupported promise of end-to-end improvement.
What the evidence says
Sourced evidence. NVIDIA Blog reports that companies in its Inception startup program are developing applications for imaging, risk assessment and treatment planning. The account describes breast cancer as the most commonly diagnosed cancer among American women and identifies wide gaps in care.
At the screening stage, the source presents limited time and a lack of nearby screening locations as practical access barriers associated with missed diagnoses. At the treatment-planning stage, it says decisions often depend on genomic assays processed by outside laboratories and that those assays can take weeks when speed and certainty are especially important.
The supported claim is therefore narrow but meaningful: participating startups are applying AI at multiple friction points along the care journey. The account does not establish that these applications form one integrated system or that they have produced particular clinical outcomes.
Operator implications
Operator analysis. The useful organizing principle is the handoff, not the model. Imaging, risk assessment and treatment planning involve different decisions, inputs and delays. Operators evaluating tools in this space should define which friction point a product addresses, who acts on its output and what happens before and after that action.
The account also suggests two distinct operating problems. Screening access concerns whether a patient can enter the care pathway. Genomic-assay turnaround concerns how quickly information becomes available after care is underway. Treating both as generic “efficiency” would obscure the different workflows and evidence needed to assess them.
A practical evaluation should keep capability, workflow adoption and clinical effect separate. A tool may generate an output, yet the source provides no basis for assuming that clinicians use it consistently, that it shortens a specific delay or that it changes patient outcomes.
Limits and open questions
This single primary account is not independently confirmed. It describes activity by startups connected to the publisher’s program, but the supplied evidence does not identify individual applications or provide results from external evaluation.
What remains unknown includes clinical validation, accuracy, deployment scale, integration with existing workflows, adoption by clinicians, effects on turnaround time and patient outcomes. The evidence also does not show whether applications spanning different stages exchange information or operate independently. Those gaps prevent conclusions about comparative performance, system-wide impact or realized improvements in care.